01
Registration and search
One record per person, found by name, phone, or identifier, with duplicate awareness and the contact details a desk actually needs.
Patients
Book at reception, open the same record at the chair, then bill the work that was completed. IvoryCRM keeps those handoffs in one place.
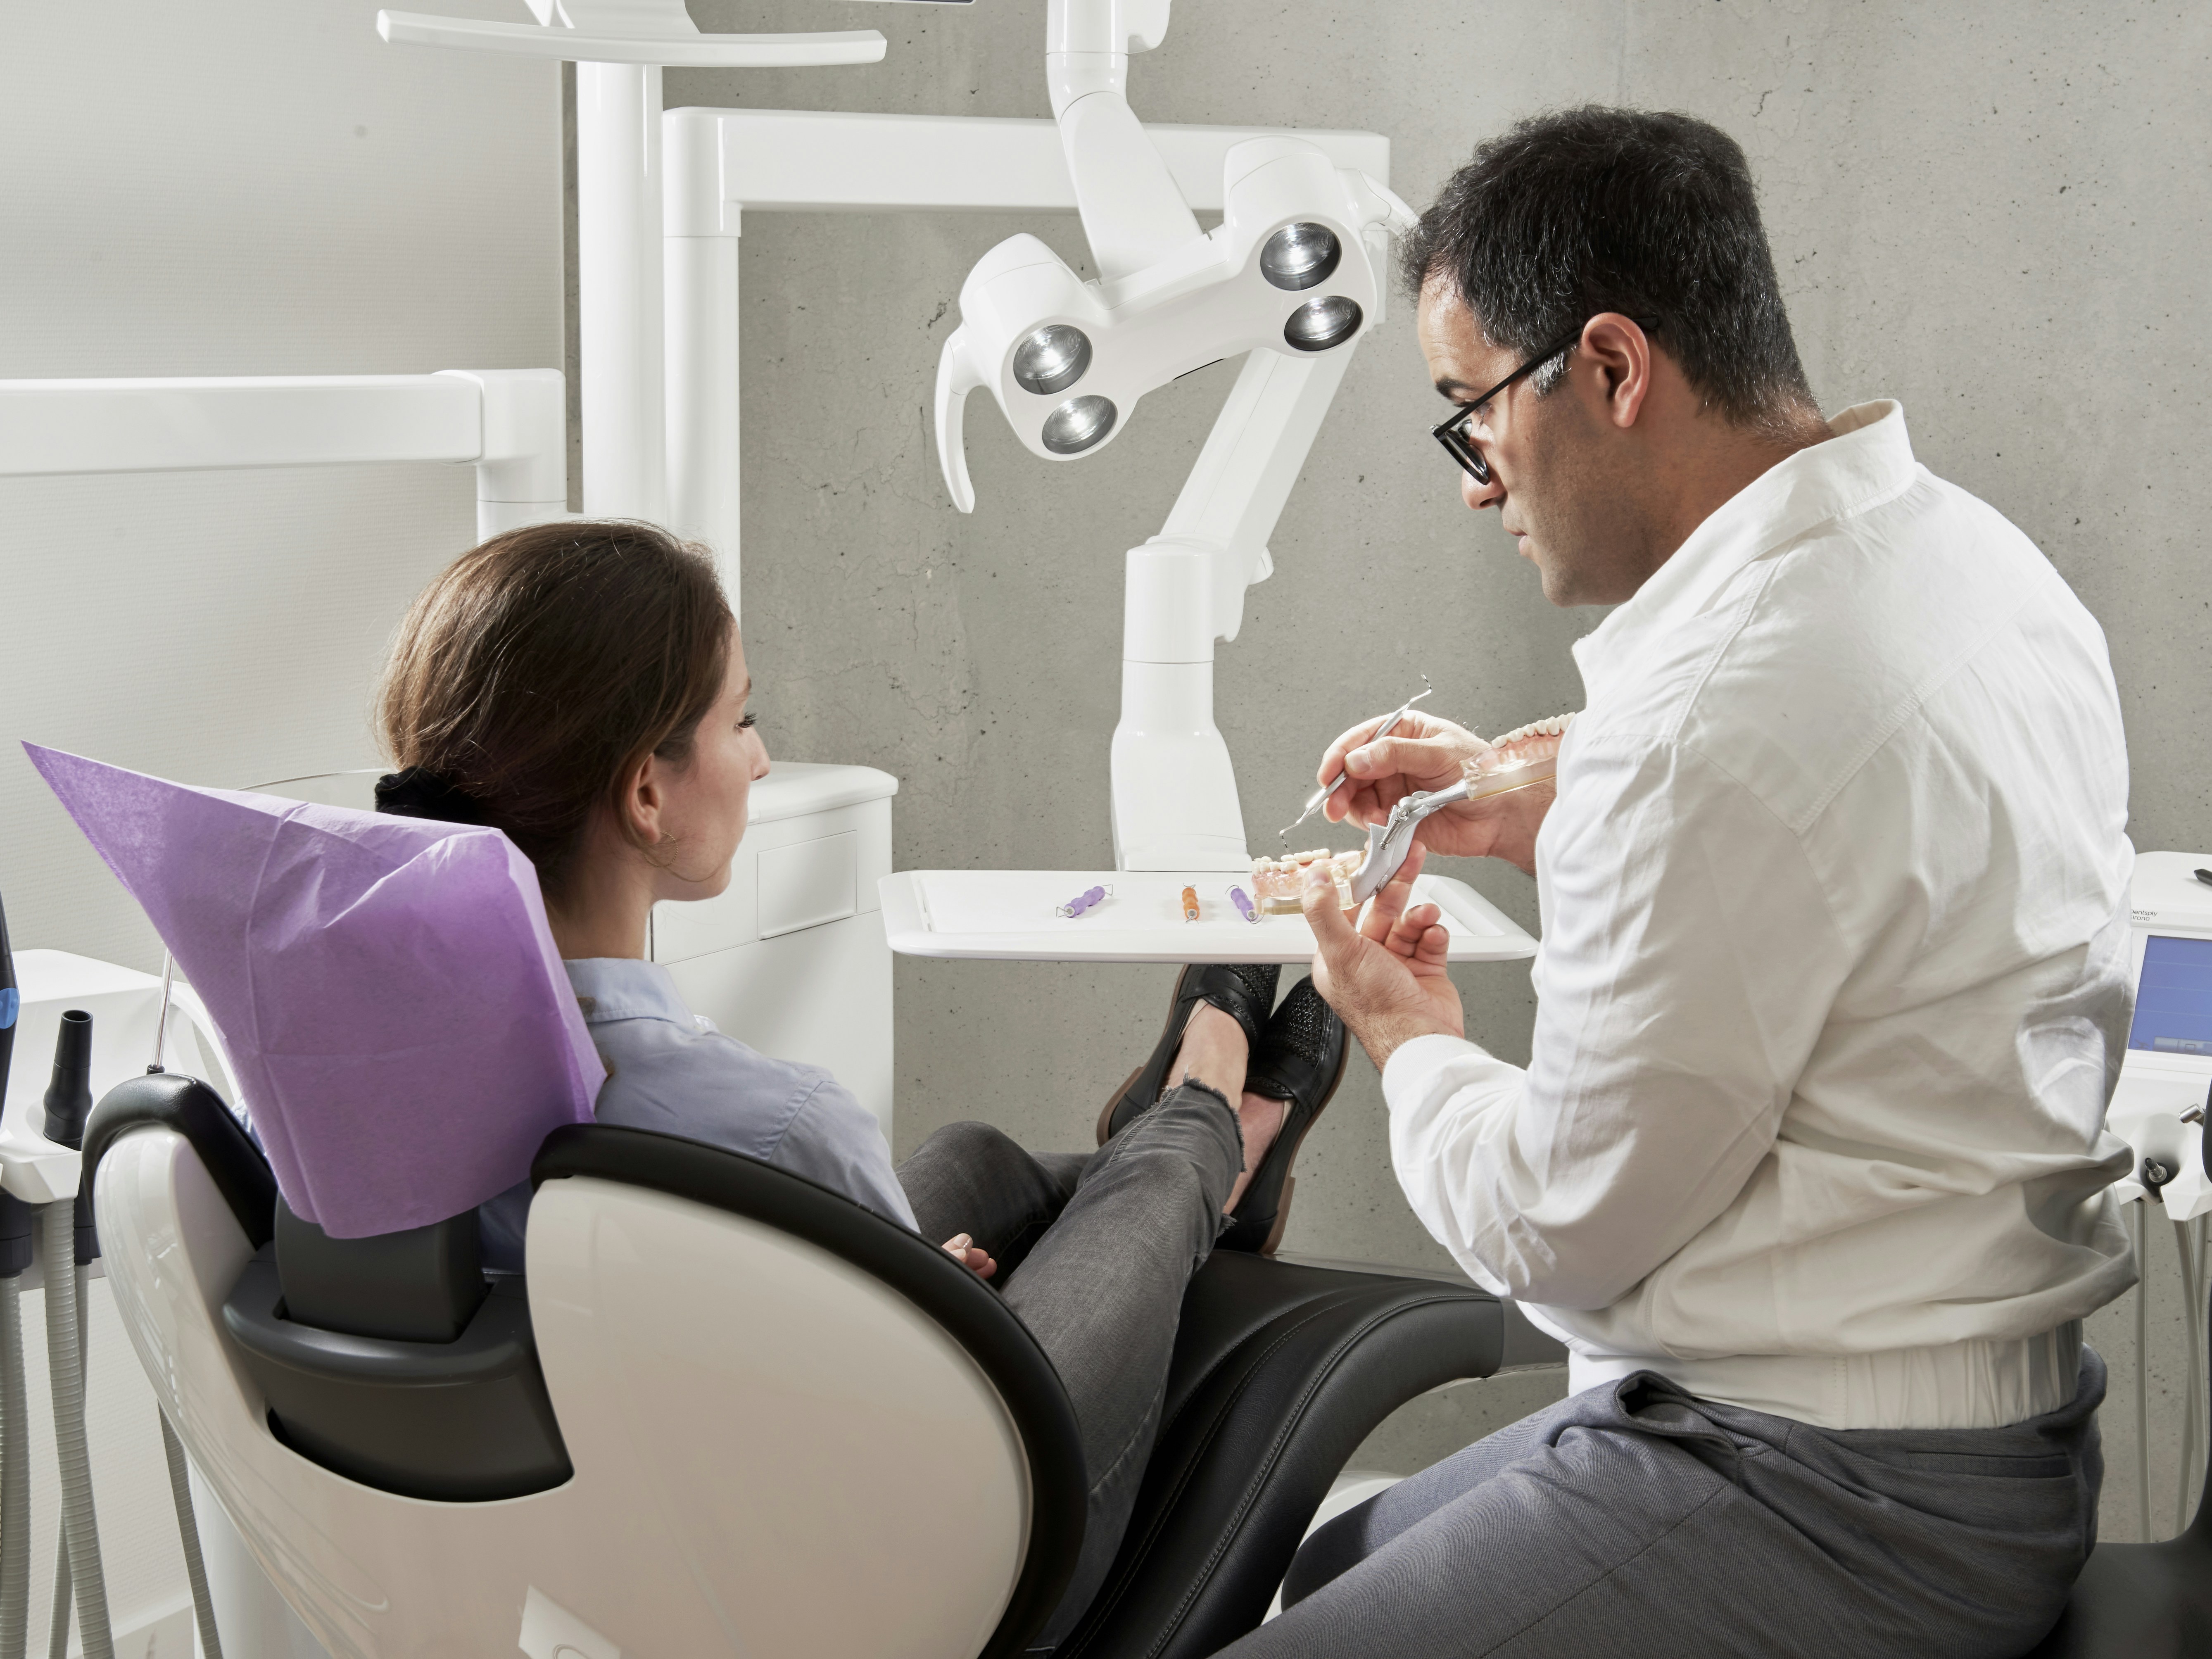
Open the patient once, then move through appointments, charting and treatment without rebuilding the record.
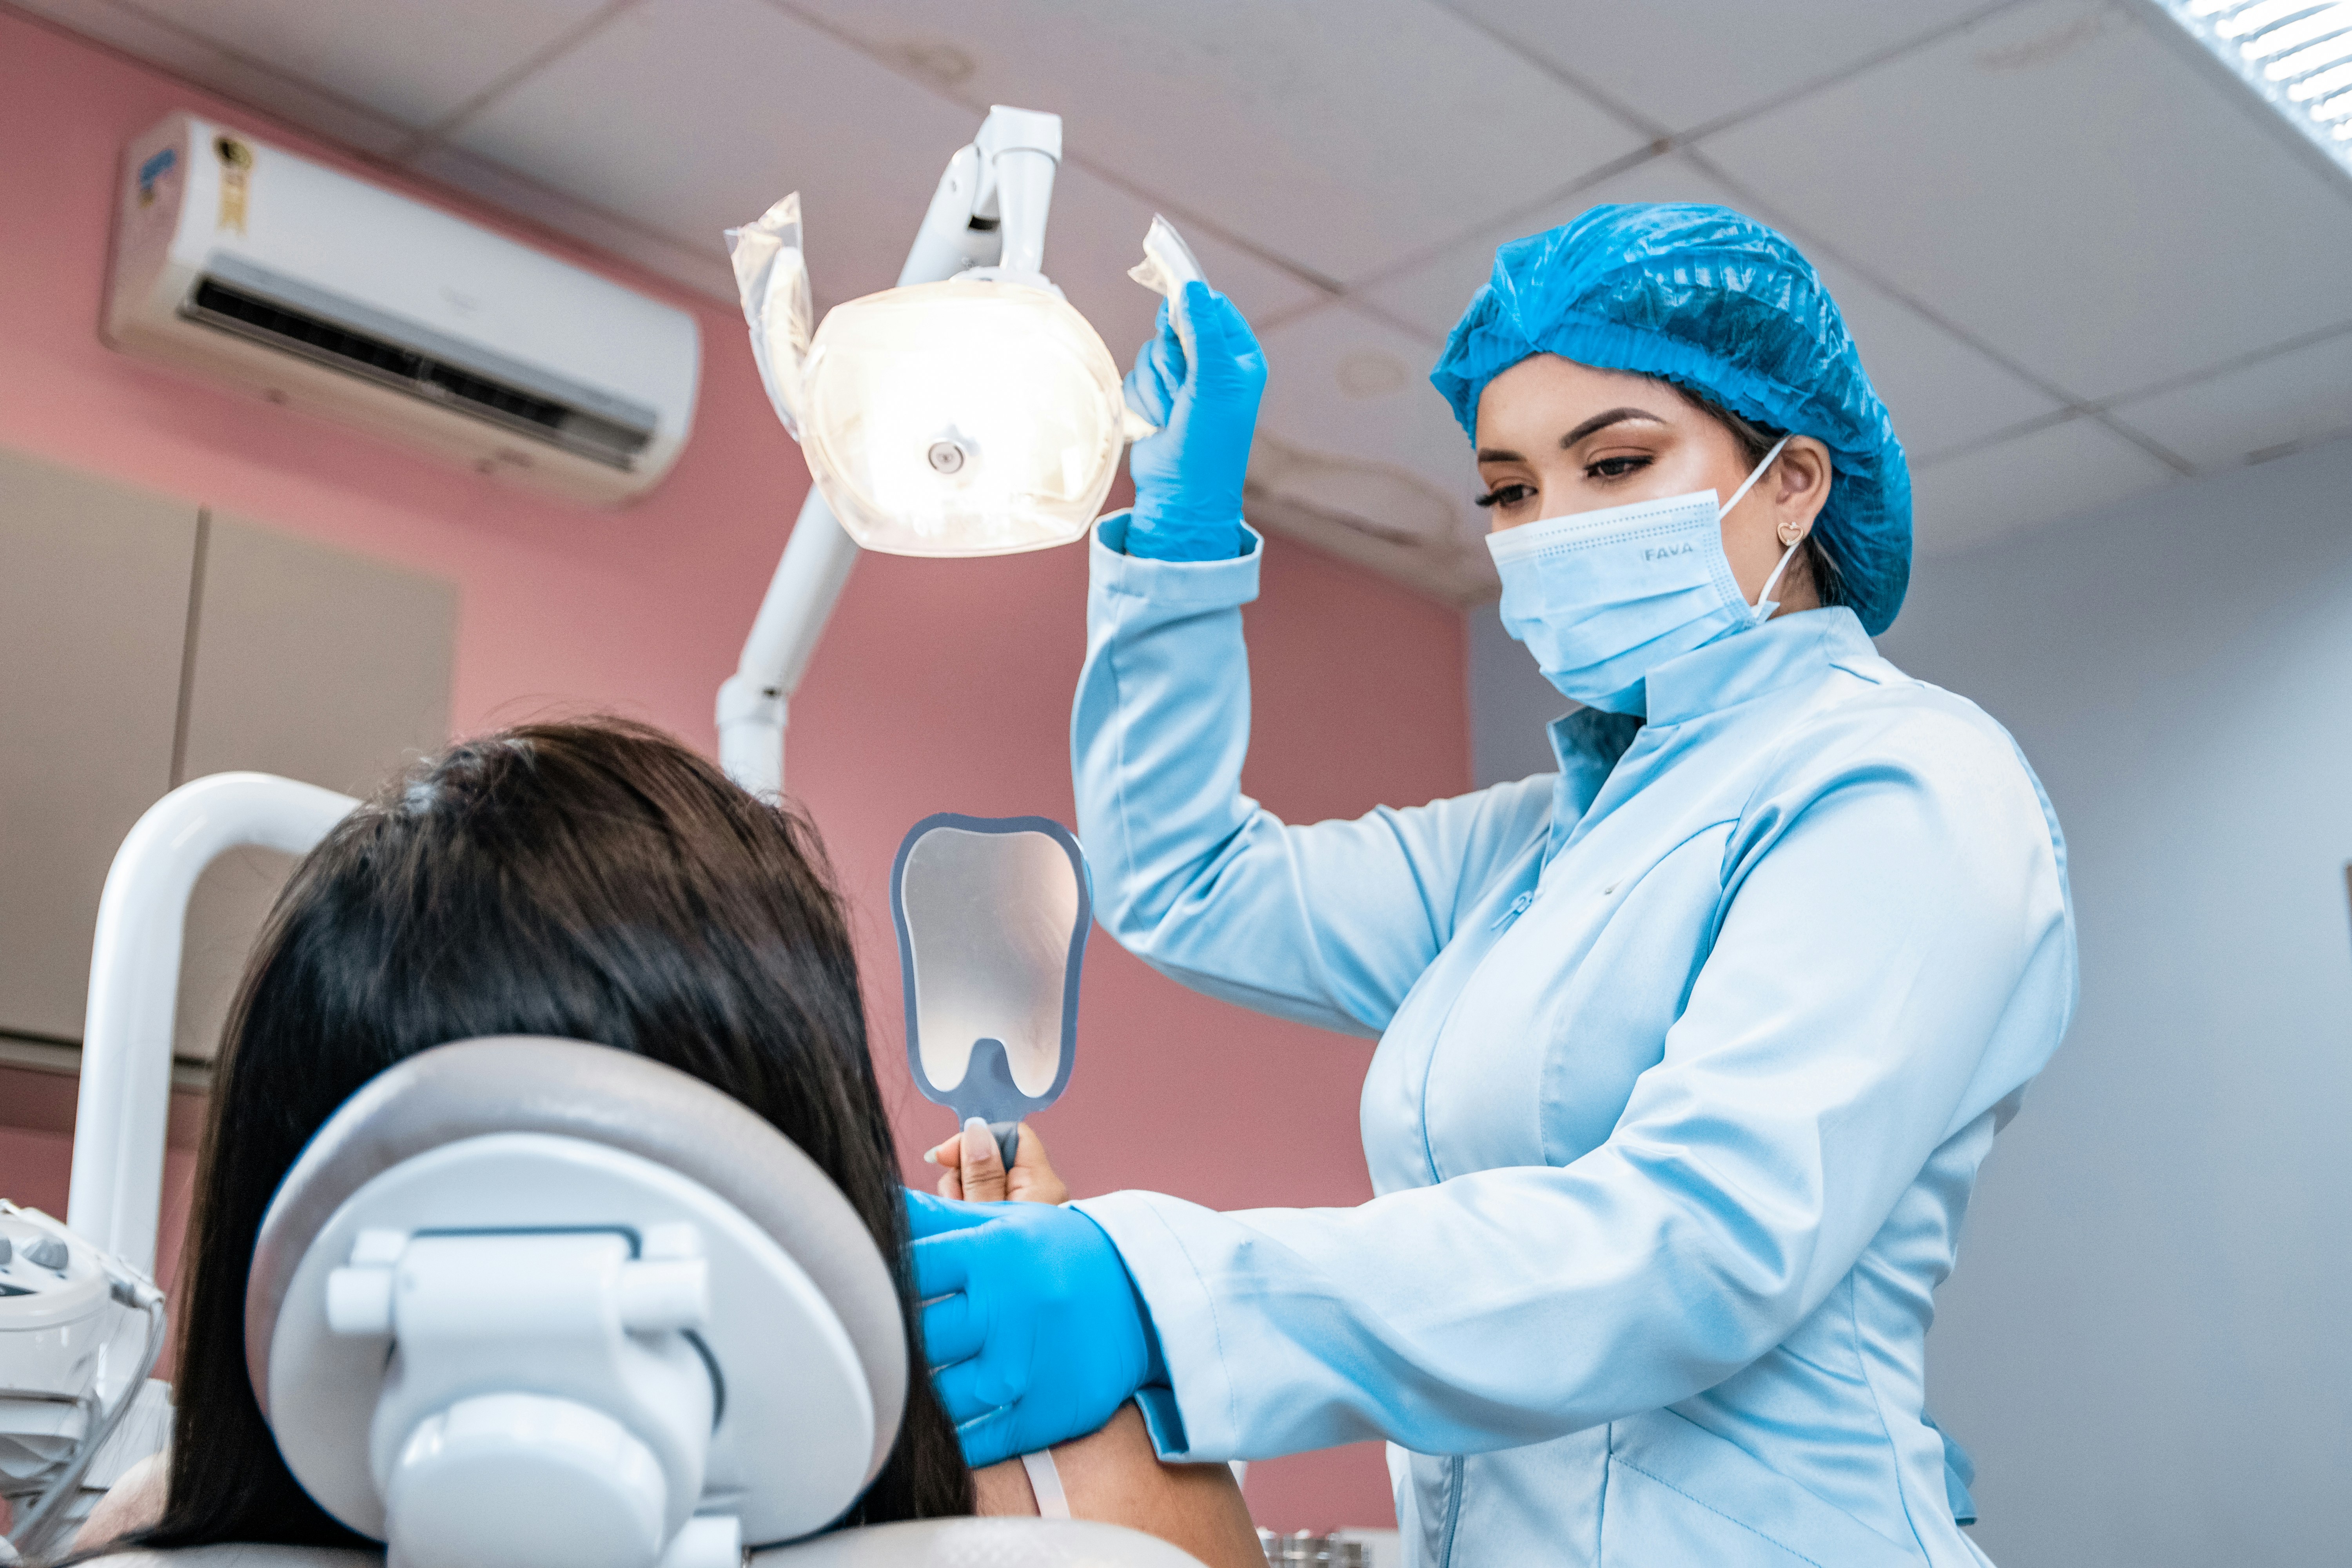
One record per person, found by name, phone, or identifier, with duplicate awareness and the contact details a desk actually needs.
Booked against an operatory, an operator, and a speciality, across branches, without double-booking a chair.
Called, seated, in chair, on hold, finished. The desk sees the position; the clinical detail stays at the chair.
An encounter opens when the patient is seated and closes when the work is done, so time in the chair is not a guess.
An odontogram in FDI notation, with surfaces, and treatments that know whether they belong to a tooth, an arch, or the whole mouth.
Perio readings charted per tooth and per site, so a comparison against last month is a real comparison.
An image is requested with a reason and a status. “Why was this taken” is the question an audit asks months later.
Plan stages for treatments such as root canals. Dates for pending stages recalculate from the previous visit’s actual completion.
Prescriptions, lab work, recalls, stock and collections remain attached to the treatment that created them.
Write, dispense and print from a formulary controlled by the clinic.
Work sent out, tracked, and returned against the patient it was made for, not against a tray of paperwork.
Who is due for a cleaning, a review, or the second half of a bridge that was never started.
Treatment is exempt healthcare; goods and cosmetic work is not. Place of supply, HSN, and the day book follow from that.
Consumables and stock movements against the procedures that actually consume them, with warnings before a chair is interrupted.
Keep each machine and its maintenance history together for the branch that uses it.
Insurance claims and practitioner payouts reconciled against the work that justified them.
See chair use, production and collections by branch or speciality.
Patient data
The database enforces this boundary on every request. The application cannot bypass it, and the test suite checks every route against another clinic’s data.
isolation and infrastructure tests
This is the failure that would end the product, so it is not left to developer discipline. It is enforced in the database, verified automatically, and stated here in full rather than reduced to a badge.
Talk through your rolloutEvery tenant table has row-level security enabled and forced. A query that forgets its tenant filter returns zero rows — not another chain’s patients.
The app connects as a role that holds no DDL and no BYPASSRLS, and refuses to start if its database role can ever bypass the policy.
Set with is_local inside the request transaction, so a pooled connection cannot carry one clinic’s tenant into the next request.
Every response is projected through an explicit allowlist. Lacking permission on a field leaves the key absent from the JSON.
CI runs a cross-tenant probe across every registered route. A new route without a probe does not merge.
Control who can open a record, handle its documents and export its data.
For a medical record, who looked matters as much as who changed it. The audit log is a first-class view, not a database table nobody opens.
Files and signed media links resolve against the patient and organisation that own them, so a shared link does not outlive its permission.
A DPDP data export is its own capability on the permission catalog, so a subject access request is a workflow rather than an incident.
Permissions compile from a catalog, so a new endpoint with no declared permission is a build failure rather than a loophole someone finds later.
Start with the workflows your team touches every day.